



Peripartum cardiomyopathy is a weakness of your heart muscle that happens in the last month of pregnancy or within five months after delivery, and doesn’t come from any other cause. This condition leads to heart failure and can be fatal. Symptoms include fatigue, heart palpitations and shortness of breath.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
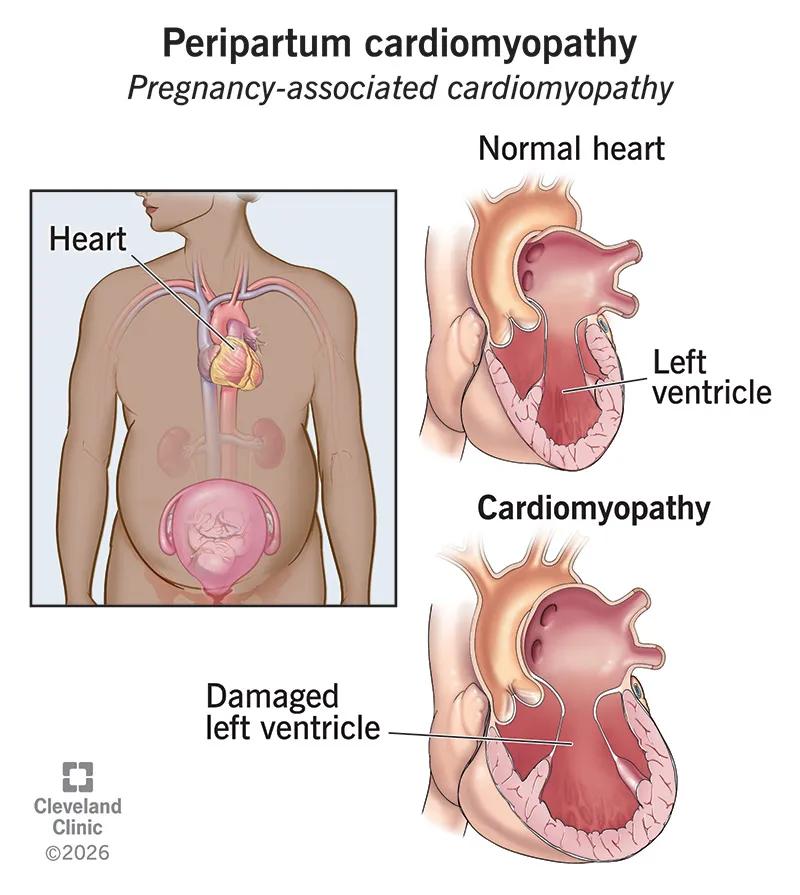
Image content: This image is available to view online.
View image online (https://assets.clevelandclinic.org/transform/0ff5a7f9-195e-4cf0-8280-1f587f0531f9/Peripartum-Cardiomyopathy-Illustration-26-HVI-8864858)
Peripartum cardiomyopathy (PPCM) is a rare condition that weakens your heart muscle during or after pregnancy. This lowers your heart’s ability to pump blood to the rest of your body (heart failure). It can be life-threatening. PPCM affects women in the last month of pregnancy or up to five months after delivery. This is why people also call it postpartum cardiomyopathy or pregnancy-associated cardiomyopathy.
Advertisement
Cleveland Clinic is a non-profit academic medical center. Advertising on our site helps support our mission. We do not endorse non-Cleveland Clinic products or services. Policy
PPCM can damage one or both of your lower heart chambers. Most commonly, it affects the left ventricle, making it hard for this chamber to pump oxygen-rich blood throughout your body. Sometimes, it can weaken both the right and left ventricles.
An early diagnosis is key for getting proper treatment and greatly increases your chances of a smooth recovery.
Peripartum cardiomyopathy isn’t common. In the U.S., it affects 1 in 1,500 to 1 in 4,000 live births. It happens more often in women older than 30 and in Black women.
Peripartum cardiomyopathy symptoms are easy to miss because many of them are like what you feel during pregnancy. Symptoms may include:
Researchers don’t know what causes peripartum cardiomyopathy. But they think possible causes include:
Peripartum cardiomyopathy has many risk factors. The more risk factors you have, the more likely you are to develop it.
Advertisement
Risk factors include:
The best way to prevent peripartum cardiomyopathy is to do what you can to keep your heart healthy. While you can’t avoid all risk factors, you can manage others by:
If you had heart failure during a previous pregnancy, talk with a healthcare provider about your risk factors if you’re planning to get pregnant again. For many women, PPCM happens more than once. If you have it with one pregnancy, you’re more likely to have it again.
As your heart gets weak and tired, it can’t pump blood as well to your organs. This affects your whole body.
Life-threatening complications may include:
Your healthcare provider will check your left ventricular ejection fraction (LVEF). They usually check this with an echocardiogram.
LVEF refers to how well your left ventricle can pump blood out of your heart. Providers describe your LVEF as a percentage, and a higher number is better. Normally, your LVEF is 50% to 70%. Peripartum cardiomyopathy reduces your LVEF to less than 45%. The lower your LVEF, the more serious the condition.
Your provider will diagnose you with PPCM if you meet all three of these criteria:
In referring to the condition, your provider may call it Class I, II, III or IV. The higher the number, the more severe your case. An early diagnosis reduces your risk of dying from PPCM and allows you to get treatment as soon as possible. If you get a diagnosis after the condition gets worse, you’re more likely to have serious complications, like continued heart problems.
Your provider will do a physical exam to look for signs of extra fluid in your body. They’ll use a stethoscope to check for abnormal heart sounds. Then, you’ll have tests that may include:
Advertisement
These tests will reveal any heart problems that you had before your pregnancy. Some people have heart problems for years and don’t know until they start having symptoms during pregnancy.
Peripartum cardiomyopathy treatment manages heart failure symptoms and helps your heart recover. The condition doesn’t go away on its own.
If you get a diagnosis during pregnancy, your provider will make sure any medications are safe for the fetus. They’ll talk with you about treatment options and discuss possible side effects. You’ll also likely work with a team of providers who can discuss the impact of heart disease on pregnancy.
You’ll probably need medications, like:
Advertisement
Rarely, you may need other treatments, like:
If you have any symptoms of peripartum cardiomyopathy, call your healthcare provider right away. You’ll have regular appointments during treatment. Once your heart is working well again, you’ll need a provider to check your heart once a year or more often. Regular checkups will help them catch the condition early if it returns.
Follow your treatment plan and call your provider to talk about any problems or changes you notice. Ask for a referral to a counselor if you feel anxious or depressed.
Call 911 or your local emergency services number, or go to the ER, if you have:
If you have peripartum cardiomyopathy, you’ll work closely with your healthcare provider to monitor your health and the fetus’s health.
Advertisement
Your provider will also create a delivery plan. If your heart failure is stable, your provider will likely prefer you have a vaginal delivery. But with PPCM, you’re more likely to have a cesarean delivery (C-section).
After delivery, you’ll keep working with your provider to manage your care. How you feel and how quickly you recover depend on many factors. The most important factor is your left ventricular ejection fraction (LVEF). If your LVEF is less than 30% at diagnosis, you’re at a higher risk of serious complications.
For some people, peripartum cardiomyopathy becomes permanent. For others, treatment can manage the symptoms and restore some or all heart function. This can take days, weeks, months or years. But you’ll likely need to keep taking medicine for at least a year after your heart function recovers.
You’ll have to monitor your health and work closely with your provider, even after your heart function returns to normal. That’s because you can have a heart failure relapse later. Also, you may still feel long-term effects, like reduced exercise capacity.
Life expectancy with peripartum cardiomyopathy depends on your condition, how well the treatment works and many other factors related to your overall health. Your risk of dying is higher with a lower ejection fraction (LVEF). Also, the outlook isn’t as good for those who need a medical device to help their heart function.
Researchers estimate that up to 3 in 10 people in the world with this condition don’t survive. In the U.S., up to 1 in 10 don’t survive.
When you’re preparing to have a baby, you don’t expect to have a heart issue at the same time. It can be overwhelming to juggle both. Your team of healthcare providers will help your heart get stronger.
If you’re pregnant and have any PPCM risk factors, talk with your provider. An early diagnosis is vital for getting the treatment you need and reducing the risk of serious complications.



Sign up for our Health Essentials emails for expert guidance on nutrition, fitness, sleep, skin care and more.
Learn more about the Health Library and our editorial process.
Cleveland Clinic’s health articles are based on evidence-backed information and review by medical professionals to ensure accuracy, reliability and up-to-date clinical standards.
Cleveland Clinic’s health articles are based on evidence-backed information and review by medical professionals to ensure accuracy, reliability and up-to-date clinical standards.
When your heart needs some help, the cardiology experts at Cleveland Clinic are here for you. We diagnose and treat the full spectrum of cardiovascular diseases.
